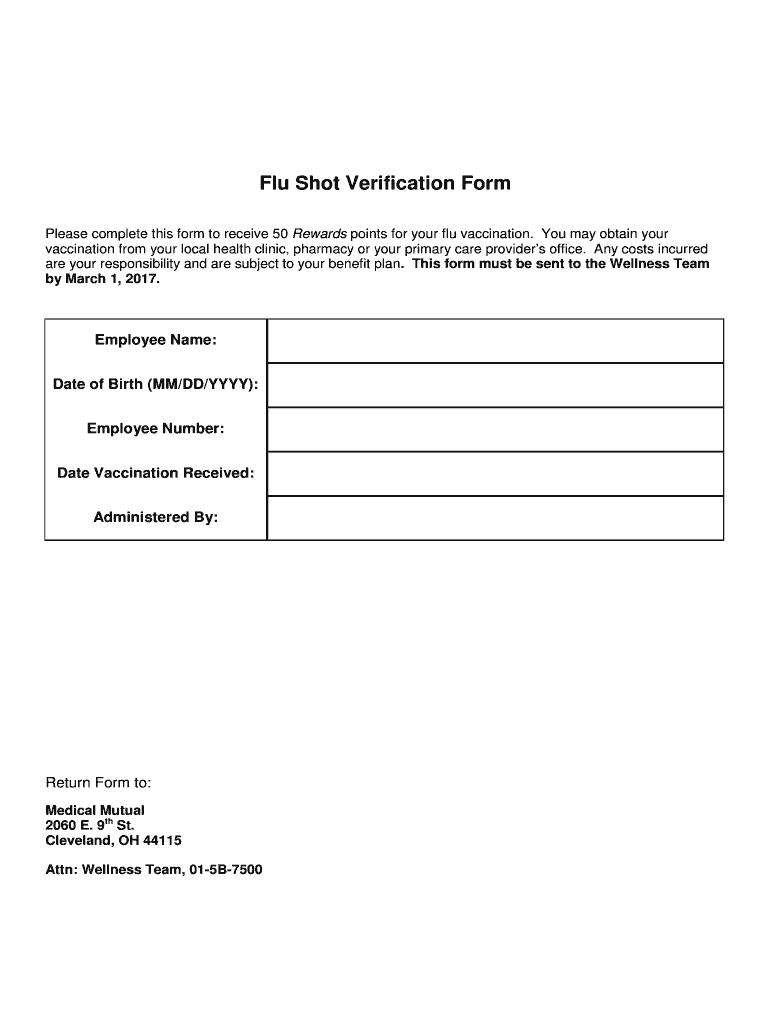
Flu Shot Verification Form - Seasonal influenza vaccination program for vha healthcare personnel. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Flu shot verification form name of employee: Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. I have read and fully understand the information on this form.
_____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. Flu shot verification form name of employee: I have read and fully understand the information on this form. Seasonal influenza vaccination program for vha healthcare personnel.
Faceing Math Template Complete with ease airSlate SignNow
_____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Flu shot verification form name of employee: Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. Seasonal influenza vaccination program for vha healthcare personnel. I have read and fully understand the information on this form.

Printable Flu Shot Verification Form Printable Word Searches
Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. Flu shot verification form name of employee: _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Seasonal influenza vaccination program for vha healthcare personnel. I have read and fully understand the information on this form.

Printable Flu Shot Verification Form Printable Word Searches
I have read and fully understand the information on this form. Seasonal influenza vaccination program for vha healthcare personnel. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Flu shot verification form name of employee:

Free Printable Flu Vaccine Consent Form prntbl
Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. Flu shot verification form name of employee: I have read and fully understand the information on this form. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Seasonal influenza vaccination program for vha healthcare personnel.

Cdc Flu VACcine Consent Form 2019 2020 Printable Consent Form
I have read and fully understand the information on this form. Seasonal influenza vaccination program for vha healthcare personnel. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. Flu shot verification form name of employee:

Certified Nursing Assistant Flu Vaccine Verification Qvcc Form
Seasonal influenza vaccination program for vha healthcare personnel. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. I have read and fully understand the information on this form. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. Flu shot verification form name of employee:

Vaccine Consent Form Template
Seasonal influenza vaccination program for vha healthcare personnel. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. I have read and fully understand the information on this form. Flu shot verification form name of employee: Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below.

Flu Shot Verification Form Form Resume Examples yKVBbNLoVM
Flu shot verification form name of employee: Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. Seasonal influenza vaccination program for vha healthcare personnel. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. I have read and fully understand the information on this form.

Proof of flu vaccine form Fill out & sign online DocHub
Flu shot verification form name of employee: I have read and fully understand the information on this form. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Seasonal influenza vaccination program for vha healthcare personnel. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below.

Cvs Printable Proof Of Flu Shot Form Printable Word Searches
Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. Seasonal influenza vaccination program for vha healthcare personnel. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. I have read and fully understand the information on this form. Flu shot verification form name of employee:
I Have Read And Fully Understand The Information On This Form.
Flu shot verification form name of employee: Seasonal influenza vaccination program for vha healthcare personnel. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below.